Small vs. Big Assisted Living: Why Intimate Settings Assistance Better ADLs
Business Name: BeeHive Homes of Albuquerque West
Address: 6000 Whiteman Dr NW, Albuquerque, NM 87120
Phone: (505) 302-1919
BeeHive Homes of Albuquerque West
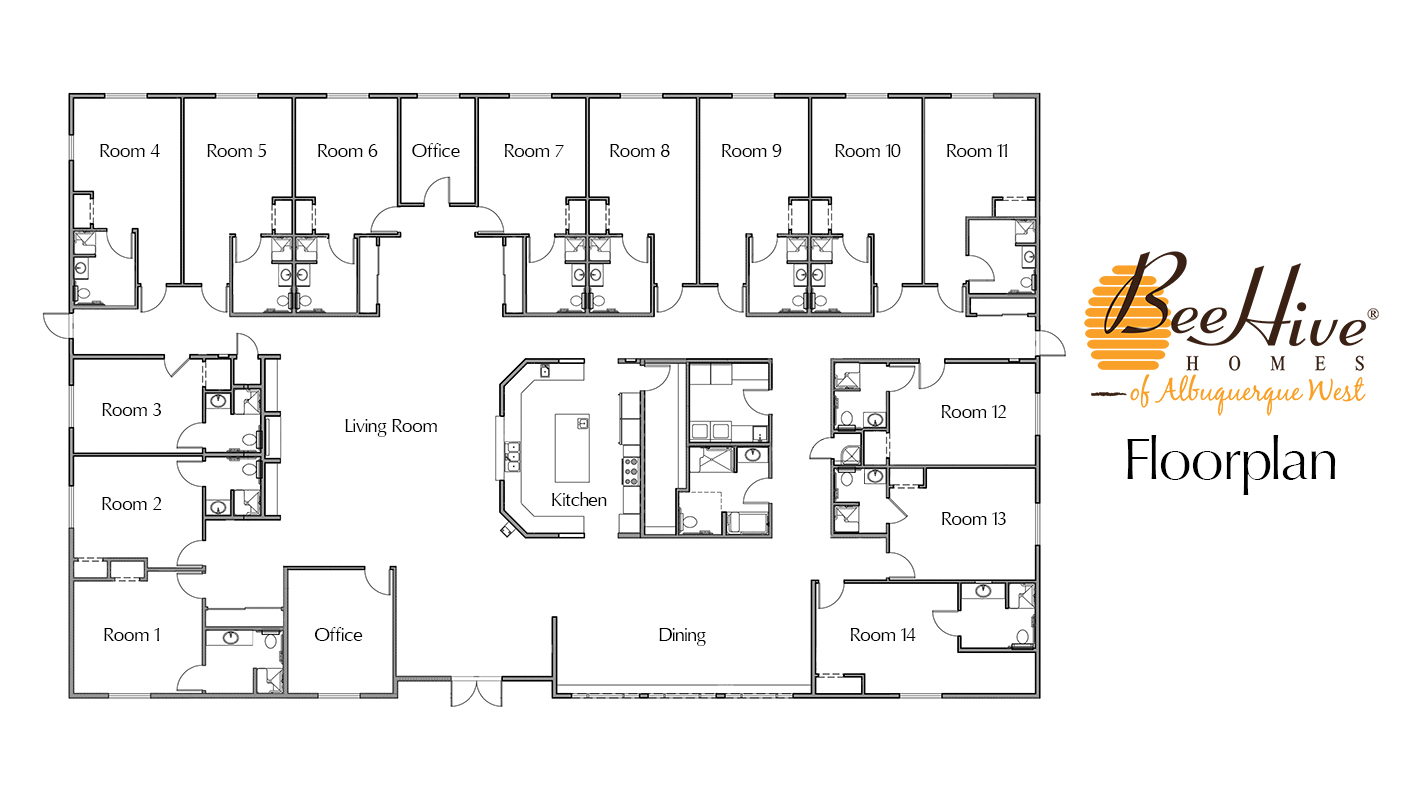
At BeeHive Homes of Albuquerque West, New Mexico, we provide exceptional assisted living in a warm, home-like environment. Residents enjoy private, spacious rooms with ADA-approved bathrooms, delicious home-cooked meals served three times daily, and the benefits of a small, close-knit community. Our compassionate staff offers personalized care and assistance with daily activities, always prioritizing dignity and well-being. With engaging activities that promote health and happiness, BeeHive Homes creates a place where residents truly feel at home. Schedule a tour today and experience the difference.
6000 Whiteman Dr NW, Albuquerque, NM 87120
Business Hours
Choosing an assisted living neighborhood is rarely just a housing decision. For a lot of families, it is a turning point in a loved one's daily life, particularly around the most individual regimens: getting dressed, bathing, handling medications, and just obtaining from bed to chair without a fall. Those Activities of Daily Living, or ADLs, are exactly where small, intimate assisted living settings frequently outperform large, campus-style communities.
I have visited, evaluated, and assisted place elders in both types of settings over the years. The pattern corresponds. Big buildings provide appealing features and hectic calendars. Small homes tend to use more dependable, more individualized help with the basics that genuinely keep someone safe and dignified. The differences are subtle on a pamphlet, and striking in real life.
This short article looks carefully at why that occurs, how to choose what your loved one really needs, and where large neighborhoods still have an edge. The goal is not to state a universal winner, however to match environment to individual, particularly around ADLs and hands-on elderly care.
What ADLs Really Mean in Daily Life
Professionals use "ADLs" constantly, so households often nod along without completely envisioning what is included. For placement decisions, it deserves decreasing and equating lingo into lived moments.
ADLs usually consist of bathing or bathing, dressing, grooming, toileting, transferring (for example, bed to chair), and consuming. Often walking or utilizing a movement gadget is contributed to the list. On paper, it sounds like a list. In real life, each ADL has layers.
Bathing is not just entering a shower. It is getting somebody to consent to bathe, changing water temperature, supporting a weak knee, washing hair thoroughly, and making certain they are completely dried to avoid skin breakdown. If your mother has dementia and hates water on her face, a rushed bath can feel like an assault. A calm, familiar caregiver who knows how to talk her through it can turn a dreaded experience into a bearable routine.
Dressing can be the trigger for agitation if somebody is pressed to rush, or it can be an opportunity for discussion and orientation. Transferring safely needs both adequate personnel and the best method, or the risk of falls increases quickly. Toileting help is deeply intimate and highly tied to dignity. Small breakdowns in any of these areas tend to snowball: avoided baths, bad hygiene, and an increased danger of urinary tract infections, falls, and hospitalizations.
Because ADLs are so relational, the staff-to-resident ratio, the speed of the environment, and the consistency of caregivers matter as much as any formal care strategy. This is where size enters play.
How Size Shapes Care: The Structural Differences
When households compare communities, they typically look first at cost, area, and look. Size lurks in the background up until you link it to what the day in fact appears like for a resident.
Large assisted living communities usually have lots, in some cases hundreds, of homeowners. Wings or floorings might be divided by level of care, memory care, or independent living. The structure frequently seems like a hotel, with a front desk, business kitchen, and formal dining room. Staffing is set up in blocks: day shift, evening, overnight. Ratios can differ widely, however numerous large properties hover around one direct care team member for 8 to 15 citizens throughout the day, with less at night.
Smaller settings can suggest different designs. Some are "residential care homes" or "board and care" homes, frequently in a transformed home with 6 to 12 citizens. Others are small lodges or cottages with 10 to 20 residents organized together. Staffing is typically more flexible and less layered. You may see one caretaker for 3 to 6 citizens during the day, plus a med tech or nurse who also knows each resident personally.
From the outdoors, a large structure may feel more excellent. Inside, size rapidly affects three things: the time a caretaker can invest with everyone, how well staff know private histories and habits, and how rapidly somebody responds when a resident needs aid with an ADL. For senior citizens who still handle almost everything by themselves, the difference may feel minor. For those needing hands-on assisted living assistance several times a day, it ends up being central.
Why Intimate Settings Tend to Support ADLs Better
Over time, I have seen small communities surpass bigger ones on ADL outcomes for 3 primary reasons: connection of relationships, slower speed, and fewer handoffs.
In a small home, the staff usually know each resident's morning rhythm. They remember that Mr. Carter requires 10 minutes to "warm up" before he can pivot safely out of bed, or that Mrs. Lee prefers to shower every other evening after her preferred program. That understanding is not just composed in a chart. It lives in the staff since they perform the very same ADLs with the same individuals day after day.
In large buildings, staffing rosters often change more regularly. A resident might see three different care aides within 2 days, especially throughout shift changes. Each aide means well, however they might not know that your father tends to get orthostatic lightheadedness when he stands too fast, or that your mother requires a calm, repeated hint to sit totally back before a transfer. That lack of familiarity appears in hurried showers, half-finished grooming, and a tendency to withdraw when a resident withstands, just because the caretaker can not invest the extra 15 minutes assisted living in albuquerque new mexico it would require to construct trust.

The physical layout matters too. In a 120-bed neighborhood, a caregiver might be accountable for two hallways and spend half their time walking from space to space. If your parent rings for help getting to the toilet, personnel may be 6 spaces away handling another resident's fall. Even a five to 10 minute hold-up can be the difference in between safe toileting and an incontinent episode that weakens self-respect and increases skin risk.
In a 10-resident home, caregivers are hardly ever more than a few actions away. They can hear somebody approaching the bathroom, or notice that Mr. Johnson did not come out for breakfast and go check. Numerous ADLs are attended to preemptively, since staff see and respond to subtle modifications before they become crises.
A Day in the Life: Big vs. Small, Through ADL Lenses
Imagining a day can clarify the compromises much better than any abstract chart.
Picture a large assisted living neighborhood. Breakfast is served from 7:30 to 9:00 in the main dining room. Transit time from a resident space may be a long corridor plus an elevator trip. One caretaker on the wing has 8 citizens needing some level of assistance up and down. The morning rapidly becomes a rush. Residents who walk separately go first. Those who require assistance dressing and transferring may not reach the dining room up until 8:45 or later on. Staff do their finest, but a resident who is slow or resistant might have their bath "pushed" to the afternoon, then to another day.
Now photo a small residential care home with 8 residents. Early morning is still a hectic time, but the environment is quieter and more flexible. Breakfast is frequently served at a family-style table near the bedrooms, and caregivers can serve homeowners in pajamas if needed, then help them dress afterward. The personnel are hardly ever more than a space away when a resident calls. ADL support becomes a series of small, continuous interactions instead of a scramble to hit scheduled tasks.
I have actually seen locals who were identified "resistant to care" in large settings move into small homes and accept bathing and dressing assist with very little protest. The behavior did not change because of a habits strategy in some abstract sense. It altered due to the fact that staff had time to technique gradually, use familiar language, adjust regimens, and develop trust.
Staff Ratios, Training, and Real-World Care
Families typically request personnel ratios as if a number alone will inform the story. Numbers matter a good deal, but context determines what they in fact mean.
In a small home with 6 residents and 2 caretakers on daytime shift, each caretaker has time to completely assist 3 people with morning ADLs, assist with meal preparation, and still respond to unscheduled requirements. If one resident has a particularly tough early morning, the other caregiver can cover. Homeowners see the same familiar faces, which supports those with dementia or anxiety.
In a large structure with 60 locals on a floor and 4 caretakers, the ratio on paper may appear comparable, however the work is more segmented. Someone might handle all showers, another may pass medications, another might be accountable for two corridors of call lights and standard ADLs. Training can be standardized and sometimes more comprehensive, which is a genuine benefit. Nevertheless, when the environment is hectic and task-driven, staff might default to "get it done" rather of "do it in the way finest fit to this person."
From a senior care point of view, training and guidance often look much better on paper in large neighborhoods. There is usually a nurse on website, official in-service training, and corporate policies. Small homes vary widely. Some are outstanding, with experienced caretakers and strong nurse oversight. Others may be thin on official training, relying more on veteran personnel who "just know" how to care for residents.
For hands-on ADLs, though, the basic question is: does my loved one get the time, repetition, and consistency needed to keep doing as much as possible for themselves, with assistance where required? Intimate settings tend to win on that, particularly for seniors who have a mix of physical and cognitive needs.
When a Large Neighborhood Might Be the Better Fit
It would be misguiding to say small is constantly much better for every single older adult. There are specific scenarios where a bigger assisted living neighborhood has clear benefits, even for residents with ADL needs.
Some elders genuinely prosper on variety, social energy, and structured activities. A retired instructor or executive who still takes pleasure in lectures, outings, and multiple clubs may feel confined in a small home with just a few fellow homeowners. Even if they require help bathing and dressing, the general lifestyle might be higher in a large, active setting.
Medical complexity is another factor. While assisted living is not the same as knowledgeable nursing, larger communities more often have 24/7 nurse existence, on-site rehabilitation, or close relationships with checking out physicians and therapists. For a resident with regular medication modifications, fragile diabetes, or a new stroke, that clinical infrastructure can be important. In those cases, you might accept some compromises on one-to-one ADL time in exchange for much better tracking and rapid response.
Cost and availability likewise matter. In some regions, there are far more big communities than small homes, or the small homes have actually restricted openings. Households often use large neighborhoods as a type of respite care, providing a short-term break to caretakers while a loved one recovers from an illness or while everyone examines longer-term options. For a planned short stay, the richness of features in a bigger setting may offset the risks of a less tailored ADL approach.
The key is to be sincere about your loved one's concerns. If they mostly require companionship, light support, and take pleasure in hectic environments, a big neighborhood can be an excellent fit. If they are modest, quickly overwhelmed, or need regular, hands-on assist with every ADL, a smaller setting normally serves them better.
The Role of Intimacy in Dementia and ADLs
Dementia makes complex every ADL. It impacts memory, sequencing, spatial awareness, language, and psychological policy. A number of the most difficult habits households report - declining showers, striking out during toileting, pacing all night - arise from stress and anxiety and confusion, not stubbornness.
In a big, unfamiliar structure, somebody with dementia can feel lost several times a day. They might forget where the restroom is, misinterpret complete strangers walking down the hallway, or feel rushed by staff who are trying to keep to a schedule. That stress and anxiety appears as resistance to care. Staff may describe the person as "hard", when in truth the environment is simply too stimulating and impersonal.
An intimate assisted living or small memory care home reduces the ranges and increases predictability. Citizens see the exact same caretakers, the same kitchen area, the very same view out the window every early morning. Caretakers can utilize consistent scripts and routines: the same joke before showers, the same warm washcloth to start face washing. Gradually, this familiarity lowers resistance and makes it possible to maintain ADLs longer, even as cognitive decrease progresses.
I keep in mind a resident who had actually been declining showers in a larger memory care unit for weeks. She clenched her fists, shouted, and tried to hit personnel. Family were told she "just does not like baths any longer." When she moved into a 10-bed home, the caregiver saw that she unwinded whenever somebody hummed a certain hymn. They developed a pre-shower ritual around that tune, rerouted her to a handheld shower she could see and control, and enabled her to hold a towel throughout her chest. Within 2 weeks, she was bathing routinely once again. Nothing in her brain changed. The environment and the method did.
For households browsing dementia, this is the heart of the small versus big concern. Intimacy and repeating are not just "nice to have" qualities. They are tools that directly support ADLs.
Practical Differences Households Will Notice
When you tour neighborhoods, some of the most telling ideas are not in the pamphlet copy, however in the small interactions you witness. In a small home, you will frequently see caretakers and citizens moving in and out of the kitchen together, sharing small talk, and starting ADLs naturally. A resident may be helped to wash up at the sink before breakfast, with a caregiver handing them a warm cloth and guiding each step.
In a big building, ADLs are more often set up and segmented. Showers may be "Monday, Wednesday, Friday at 10:30," and if your mother refused at 10:35, she might not get another effort until the next scheduled day. Meals are at set times, and late sleepers may get "room trays" if they miss the window, typically without the very same level of social engagement or support with eating.
Noise level, lighting, and space design matter for ADL success. Small homes tend to feel locally familiar, which lowers stress and anxiety for lots of seniors. Bright overhead lights and long corridors can be disorienting, particularly for those with poor vision or cognitive decrease. In a small setting, personnel can more easily modify the environment. They may reduce the lights during night care, play soft music throughout bathing times, or keep adaptive devices within reach.
Families likewise see how quickly patterns are picked up. In small settings, if your father battles with buttons, somebody will most likely suggest pull-over shirts by the 2nd or 3rd day, and you will see that reflected in how they assist him dress. In a big setting, the exact same observation may be buried amidst many locals' needs, unless you or a strong advocate presses it into the written care plan and follows up.
A Simple Contrast Checklist for ADL Support
When you tour or assess options, it assists to have a concentrated lens on ADLs, not just visual appeal or activity calendars. Use this short list to compare how small and big settings may feel for your loved one:
- Ask personnel to describe a typical early morning for a resident who requires assist with bathing, dressing, and toileting. Listen for just how much time they permit, and whether the routine noises hurried or versatile.
- Observe how personnel address locals in passing. Do they utilize names, touch, and eye contact, or are they mainly task focused and in a rush between rooms?
- Check how far spaces are from restrooms and dining locations. Envision your loved one making that journey 3 or four times a day.
- Ask how they adapt routines for somebody who refuses or fears bathing. Search for specific, concrete examples, not vague peace of minds.
- Inquire about staff continuity. Do the same caretakers generally care for the exact same locals, or do projects change frequently?
You are listening less for polished responses and more for consistency, detail, and indications that personnel genuinely understand their locals as individuals.
The Function of Respite Care in Screening Fit
One underused technique for families is to deal with respite care as a trial run. Lots of assisted living communities, both large and small, deal short stays varying from a couple of days to a couple of weeks. Throughout that time, your loved one lives in the community as a momentary resident, receiving the exact same senior care and elderly care services as long-term residents.
For ADLs, respite stays are incredibly revealing. You will see how rapidly personnel discover your parent's regimens, how frequently call lights are addressed, whether clothes are put away effectively, and if health and grooming look preserved. Families sometimes discover that the impressive large community has a hard time to manage particular behaviors or ADL tasks, while a simple small home manages them efficiently. Other times, the reverse takes place, specifically if your loved one is more social and independent than you realized.
Respite care likewise gives your parent a voice. Even an individual with moderate cognitive decrease can frequently tell you whether they feel cared for, rushed, lonesome, or safe. Focus on whether they discuss "the people" by name in a small home, versus "the location" or "the building" in a larger one. That psychological connection typically correlates highly with ADL success.
Balancing Dignity, Safety, and Independence
At the heart of all these decisions is a balancing act: dignity, safety, and independence. Small, intimate assisted living settings tend to protect dignity and safety by carefully supporting ADLs and reducing the possibility of lapses. They also, when succeeded, support self-reliance by providing locals just enough assist, not too much.
A great caretaker in a small home will know that Mrs. Daniels can still brush her teeth separately if someone simply sets out the tooth brush and hints her to start. In a busier environment, that same resident might have her teeth brushed for her due to the fact that staff are pushed for time. Over weeks and months, that distinction accelerates decline.
Large communities, when truly well staffed and well led, can absolutely maintain strong ADL assistance. Some attain this by producing small "areas" within a bigger school, restricting each caretaker's location and motivating relationship-based care. Others buy advanced training in dementia care methods and work with sufficient personnel to avoid chronic hurrying. These models sit closer to the "finest of both worlds," however they tend to be at the greater end of the expense spectrum.
In completion, your option will hardly ever have to do with perfection. It will have to do with compromises. Amenities versus intimacy. Variety versus predictability. On-site services versus everyday one-to-one time. For older grownups who need constant, hands-on assist with bathing, dressing, toileting, and mobility, smaller, more intimate settings often tip the scales, due to the fact that they convert personnel hours into real, tailored care.
Questions to Ask Yourself Before Deciding
As you weigh alternatives, it assists to go back from marketing language and ask yourself a few grounded concerns about ADL assistance:
- Which environment will permit staff to truly understand my loved one's practices, fears, and choices around bathing, dressing, and toileting?
- If something fails - a fall, a rejection to shower, a bout of confusion - where are staff most likely to have time to problem-solve rather than default to crisis mode?
- Does my loved one gain more from day-to-day social variety or from predictable, familiar faces directing them through vulnerable jobs?
- How much am I counting on amenities to make me feel better versus what my loved one in fact uses and delights in?
- Could a short respite care remain in a couple of settings assist us see which environment much better supports ADLs in practice?
Clear responses to these questions generally point highly toward either a small or large setting as the better first choice.

The choice about assisted living positioning is one of the most personal in senior care. By focusing on how each environment really handles ADLs, instead of only on appearances or activity calendars, you offer your loved one the best possibility at a life that feels safe, respectful, and as independent as possible.
BeeHive Homes of Albuquerque West provides assisted living care
BeeHive Homes of Albuquerque West provides memory care services
BeeHive Homes of Albuquerque West provides respite care services
BeeHive Homes of Albuquerque West offers support from professional caregivers
BeeHive Homes of Albuquerque West offers private bedrooms with private bathrooms
BeeHive Homes of Albuquerque West provides medication monitoring and documentation
BeeHive Homes of Albuquerque West serves dietitian-approved meals
BeeHive Homes of Albuquerque West provides housekeeping services
BeeHive Homes of Albuquerque West provides laundry services
BeeHive Homes of Albuquerque West offers community dining and social engagement activities
BeeHive Homes of Albuquerque West features life enrichment activities
BeeHive Homes of Albuquerque West supports personal care assistance during meals and daily routines
BeeHive Homes of Albuquerque West promotes frequent physical and mental exercise opportunities
BeeHive Homes of Albuquerque West provides a home-like residential environment
BeeHive Homes of Albuquerque West creates customized care plans as residents’ needs change
BeeHive Homes of Albuquerque West assesses individual resident care needs
BeeHive Homes of Albuquerque West accepts private pay and long-term care insurance
BeeHive Homes of Albuquerque West assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Albuquerque West encourages meaningful resident-to-staff relationships
BeeHive Homes of Albuquerque West delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Albuquerque West has a phone number of (505) 302-1919
BeeHive Homes of Albuquerque West has an address of 6000 Whiteman Dr NW, Albuquerque, NM 87120
BeeHive Homes of Albuquerque West has a website https://beehivehomes.com/locations/albuquerque-west/
BeeHive Homes of Albuquerque West has Google Maps listing https://maps.app.goo.gl/R1bEL8jYMtgheUH96
BeeHive Homes of Albuquerque West has Facebook page https://www.facebook.com/BeehiveABQW/
BeeHive Homes of Albuquerque West won Top Assisted Living Homes 2025
BeeHive Homes of Albuquerque West earned Best Customer Service Award 2024
BeeHive Homes of Albuquerque West placed 1st for Senior Living Communities 2025
People Also Ask about BeeHive Homes of Albuquerque West
What is BeeHive Homes of Albuquerque West monthly room rate?
Our base rate is $6,900 per month, but the rate each resident pays depends on the level of care that is needed. We do an initial evaluation for each potential resident to determine the level of care needed. The monthly rate is based on this evaluation. We also charge a one-time community fee of $2,000.
Can residents stay in BeeHive Homes of Albuquerque West until the end of their life?
Usually yes. There are exceptions, such as when there are safety issues with the resident, or they need 24 hour skilled nursing services.
Does Medicare or Medicaid pay for a stay at Bee Hive Homes?
Medicare pays for hospital and nursing home stays, but does not pay for assisted living as a covered benefit. Some assisted living facilities are Medicaid providers but we are not. We do accept private pay, long-term care insurance, and we can assist qualified Veterans with approval for the Aid and Attendance program.
Do we have a nurse on staff?
We do have a nurse on contract who is available as a resource to our staff but our residents' needs do not require a nurse on-site. We always have trained caregivers in the home and awake around the clock.
Do we allow pets at Bee Hive?
Yes, we allow small pets as long as the resident is able to care for them. State regulations require that we have evidence of current immunizations for any required shots.
Do we have a pharmacy that fills prescriptions?
We do have a relationship with an excellent pharmacy that is able to deliver to us and packages most medications in punch-cards, which improves storage and safety. We can work with any pharmacy you choose but do highly recommend our institutional pharmacy partner.
Do we offer medication administration?
Our caregivers are trained in assisting with medication administration. They assist the residents in getting the right medications at the right times, and we store all medications securely. In some situations we can assist a diabetic resident to self-administer insulin injections. We also have the services of a pharmacist for regular medication reviews to ensure our residents are getting the most appropriate medications for their needs.
Where is BeeHive Homes of Albuquerque West located?
BeeHive Homes of Albuquerque West is conveniently located at 6000 Whiteman Dr NW, Albuquerque, NM 87120. You can easily find directions on Google Maps or call at (505) 302-1919 Monday through Sunday 10am to 7pm
How can I contact BeeHive Homes of Albuquerque West?
You can contact BeeHive Homes of Albuquerque West by phone at: (505) 302-1919, visit their website at https://beehivehomes.com/locations/albuquerque-west, or connect on social media via Facebook
The Indian Pueblo Cultural Center offers engaging exhibits and cultural education ideal for assisted living and memory care residents during senior care or respite care outings.